

Doctor explains: MCAS (Mast Cell Activation Syndrome) and ME/CFS — Understanding the Possible Overlap


People with ME/CFS often experience a wide range of symptoms that can involve several body systems. Fatigue, brain fog, sleep problems, dizziness, headaches, gastrointestinal symptoms and sensitivity to foods or medications may occur together.
One condition that is increasingly discussed in this context is Mast Cell Activation Syndrome (MCAS).
As an ME/CFS specialist, I am sometimes asked whether MCAS could explain symptoms that occur alongside ME/CFS, whether the two conditions can coexist, and whether treating mast-cell-related symptoms can improve quality of life.
The answer is that there may be an overlap, but MCAS should not automatically be assumed to be the cause of ME/CFS symptoms.
What is MCAS?
Mast cells are immune cells that help protect the body. They are involved in allergic reactions, inflammation and responses to infections or other triggers.
When mast cells become activated, they release substances such as histamine and other inflammatory mediators.
Mast Cell Activation Syndrome describes a situation in which mast-cell activation is excessive or inappropriate and produces recurrent symptoms affecting different parts of the body.
Symptoms can include:
Flushing or unusual skin reactions
Itching or hives
Swelling
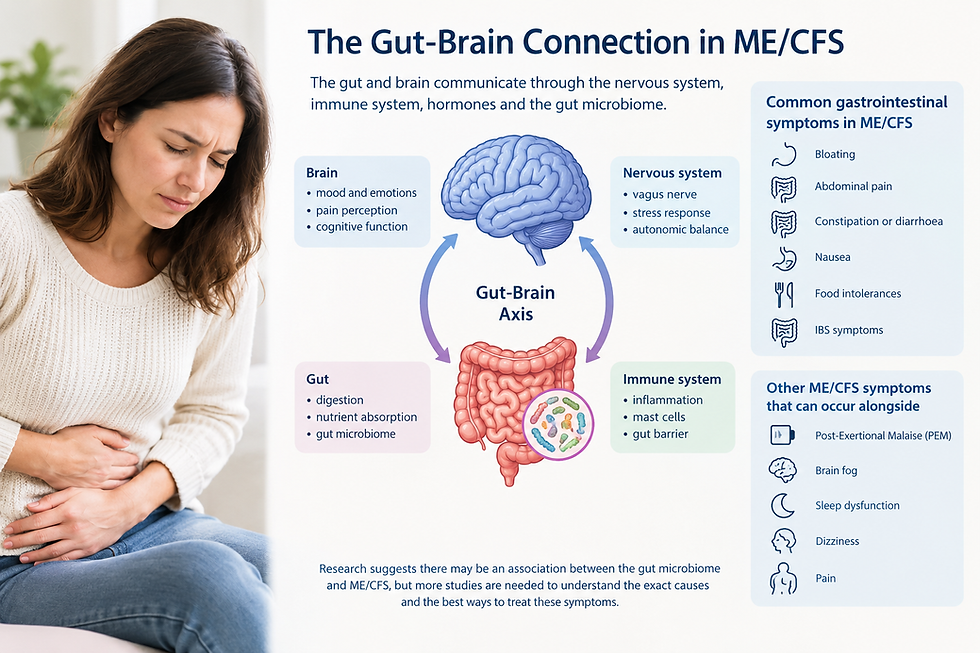
Abdominal pain, diarrhoea or nausea
Reactions to particular foods
Nasal or respiratory symptoms
Headaches
Palpitations or changes in blood pressure
Dizziness or feeling faint
Increased sensitivity to medications or environmental triggers
Importantly, having one or more of these symptoms does not by itself mean that someone has MCAS.
Post-Exertional Malaise (PEM) and MCAS: why the distinction matters
One of the most important features of ME/CFS is Post-Exertional Malaise (PEM).
PEM is a worsening of symptoms after physical, cognitive, emotional or other exertion. The deterioration may be delayed and can last for days or considerably longer.
This is different from simply feeling tired after activity.
Some people with ME/CFS and suspected MCAS report that exertion, heat, stress, particular foods or other triggers can produce a combination of symptoms. This can make it difficult to determine which symptoms are attributable to ME/CFS, MCAS, another condition, or several conditions occurring together.
Understanding this distinction is important when considering Post-Exertional Malaise (PEM) management.
Pacing and staying within an individual's energy limits remain important when PEM is present, regardless of whether MCAS is also suspected.
Post-Exertional Malaise (PEM), flushing and food reactions
There can be considerable symptom overlap between ME/CFS and mast-cell-related conditions.
For example, a person may experience fatigue and brain fog together with flushing, itching, gastrointestinal symptoms or reactions to particular foods.
However, these symptoms do not provide a simple diagnostic test for MCAS.
A careful assessment should consider the complete pattern, including:
When symptoms started
Whether there is clear Post-Exertional Malaise (PEM)
Whether symptoms are episodic or persistent
Possible food, medication or environmental triggers
Gastrointestinal symptoms
Skin symptoms
Cardiovascular symptoms such as dizziness or palpitations
Allergy history
Sleep problems
Orthostatic intolerance
Other medical conditions and medications
This is where a differential diagnosis for chronic fatigue syndrome is particularly important.
Is MCAS common in ME/CFS?
The relationship between MCAS and ME/CFS remains an area of active ME/CFS research.
Some researchers have proposed that mast-cell activation, immune signalling and inflammatory pathways could contribute to symptoms in subsets of people with ME/CFS. Similar questions are being investigated in people with Long COVID, sometimes referred to as the Long COVID and ME/CFS connection.
However, the evidence does not currently justify diagnosing MCAS in every person with ME/CFS.
There is also no single blood test that can simply confirm that someone's ME/CFS symptoms are caused by MCAS.
This is an important distinction between research findings and individual clinical diagnosis.
Post-Exertional Malaise (PEM) and orthostatic intolerance
Another reason these conditions can become difficult to separate is that people with ME/CFS may experience autonomic symptoms.
Orthostatic intolerance symptoms in ME/CFS can include dizziness, light-headedness, palpitations, weakness, nausea and difficulty remaining upright.
Some patients are investigated for conditions such as POTS or other forms of dysautonomia.
If someone has significant orthostatic symptoms, this should be assessed separately rather than automatically attributed to MCAS.
A comprehensive assessment may therefore need to consider ME/CFS, autonomic dysfunction, allergy-related conditions, gastrointestinal disorders, medication effects and other possible explanations.
Post-Exertional Malaise (PEM) management when several conditions overlap
When someone has ME/CFS together with another condition, management usually needs to be personalised.
The first principle is to avoid repeatedly pushing through Post-Exertional Malaise (PEM).
Patients often ask how to recover from a post-exertion malaise crash. Unfortunately, there is no guaranteed rapid treatment. During a crash, reducing activity and allowing adequate recovery may be more appropriate than trying to exercise through symptoms.
For people with severe illness, micro-pacing strategies for severe ME may be more appropriate than conventional activity programmes.
Importantly, treatments that deliberately increase activity despite PEM are not considered appropriate treatment for ME/CFS.
This is why discussions around non-GET safe therapies for ME/CFS are particularly important.
Can MCAS be treated?
Treatment depends on whether there is a convincing clinical diagnosis and what symptoms are present.
Management may include identifying and avoiding individual triggers, where practical, together with treatments directed at specific symptoms. Antihistamines and other medications affecting mast-cell mediators are sometimes used in appropriate patients, but they are not suitable for everyone and should be discussed with a clinician.
It is also important not to assume that supplements, restrictive diets or so-called functional medicine for chronic fatigue approaches are automatically safe or effective.
Similarly, treatments sometimes discussed online—including Low Dose Naltrexone (LDN) for ME/CFS, vagus nerve stimulation, mitochondrial support and other experimental approaches—should be considered in the context of the available evidence and an individual's circumstances.
At present, there is no universally proven medication that cures ME/CFS or MCAS.
When should you seek specialist assessment?
Consider discussing your symptoms with a doctor if you have persistent unexplained fatigue, particularly if you also experience clear Post-Exertional Malaise (PEM).
Specialist assessment can be particularly useful when symptoms are complex or when several possible diagnoses overlap.
An online ME/CFS doctor or ME/CFS telehealth doctor can review your symptom history, previous investigations, medications and functional limitations and help determine whether further assessment is appropriate.
A specialist consultation may also be useful for people looking for a private ME CFS clinic online, a chronic fatigue syndrome specialist, a post viral fatigue doctor, or assessment following Long COVID.
For people who primarily have widespread pain and fatigue, assessment by a fibromyalgia specialist online may also be appropriate.
The aim should not simply be to attach another diagnosis. It is to understand the overall pattern of symptoms and identify appropriate, evidence-informed management.
What about ME/CFS testing?
There is currently no single routine diagnostic blood test that confirms ME/CFS.
ME/CFS testing generally involves assessing symptoms against recognised diagnostic criteria while excluding other conditions that could explain them.
Research into biomarkers and new approaches to ME/CFS testing is ongoing. As an ME/CFS researcher as well as a clinician, I am particularly interested in research that could eventually improve diagnosis and help identify biologically meaningful patient subgroups.
The same principle applies to MCAS: testing should be guided by the clinical picture rather than performed simply because a patient has fatigue.
The key message about MCAS and Post-Exertional Malaise (PEM)
MCAS and ME/CFS may coexist, and there can be substantial symptom overlap. However, suspected mast-cell activation should not automatically be used to explain every symptom in someone with ME/CFS.
The most useful starting point is a careful clinical assessment.
For people with ME/CFS, recognising Post-Exertional Malaise (PEM) remains particularly important. Understanding your own limitations and developing an appropriate management plan can be more useful than continually searching for a single explanation for every symptom.
As ME/CFS research, ME/CFS testing and ME/CFS therapy continue to develop, our understanding of these overlapping conditions will hopefully become clearer.
You can also explore the clinic's ME/CFS and related conditions information and read more about ME/CFS research, ME/CFS testing and ME/CFS therapy on the UK ME/CFS Specialist blog.
If you would like to discuss whether your symptoms fit ME/CFS, fibromyalgia, Long COVID or another post-viral condition, you can book an online specialist consultation or learn more about Prof. Dmitry Pshezhetskiy and his clinical and research work.
Prof. Dmitry Pshezhetskiy, MBBS, PhD, MRCGP
GMC 7494518 — Registered Medical Practitioner (GP)
Medical Disclaimer: The information provided in this article is for general educational and informational purposes only and does not constitute personalized medical advice, formal diagnosis, or treatment planning. Reading this content or communicating via this website does not establish a doctor-patient relationship with Prof Dmitry Pshezhetskiy. ME/CFS affects every individual differently; strategies discussed may not be suitable or safe for your specific health situation. Always consult your GP, specialist healthcare team, or NHS 111 regarding your personal medical concerns. In a medical emergency, please dial 999 or visit your nearest Emergency Department immediately. For a full disclaimer, see Medical Disclaimer & Terms of Use in Terms and Conditions on the policies page.
If you would like specialist assessment, learn more about our online consultations.


Comments